
ISO 9001:2015 Bureau Veritas / UKASGujarat CEA Permanent registrationICMR ART Level-2 laboratoryESHRE / ASRM aligned careISUOG IDEA imaging protocol15-bed single-speciality hospital★ 5.0 · 250+ Google reviews
Minimal-access gynaecologic surgery performed on the Karl Storz 3D laparoscopy system — true stereoscopic visualisation, German precision optics, and depth perception that materially improves outcomes in endometriosis excision, deep pelvic dissection, and fine suturing. Dr. Priyadatt Patel performs advanced laparoscopy for endometriosis, fibroids, adenomyosis, ovarian cysts, ectopic pregnancy, tubal disease, and hysterectomy — under ESGE and AAGL standards, with anatomical respect as the first principle.
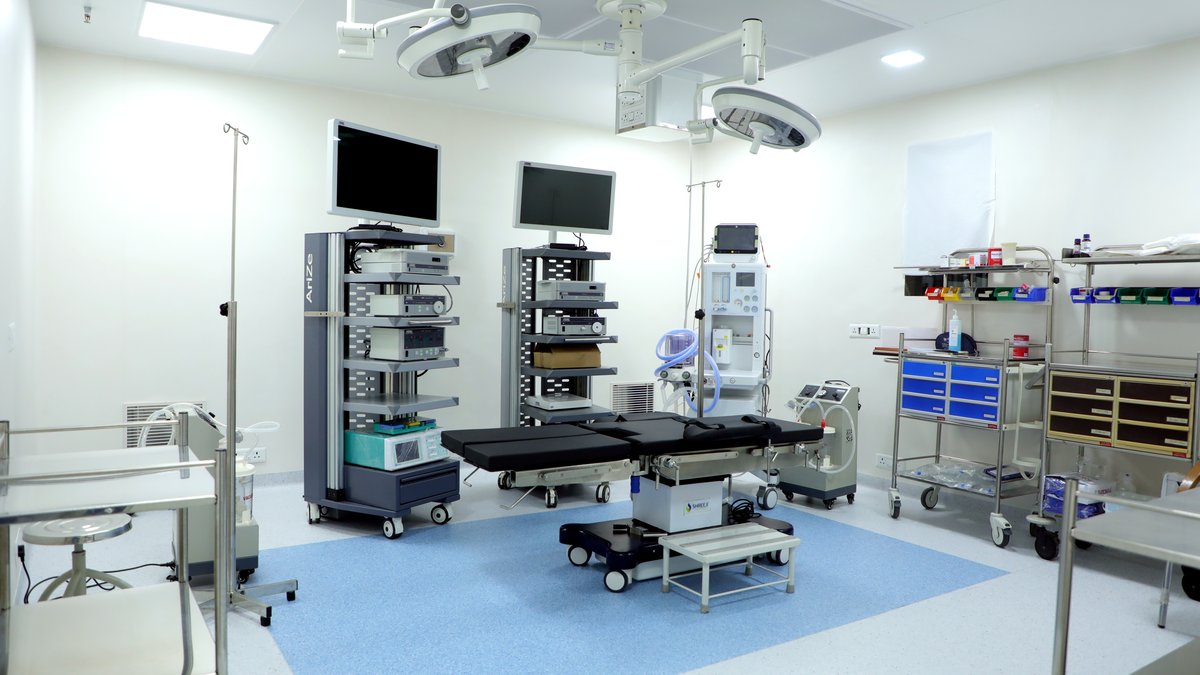
Karl Storz 3D Laparoscopy System · Class 100 OT · Advanced Energy Sources · Multi-disciplinary Backup · Anaesthesia + Ventilator Workstation
Not every gynaecological condition needs surgery — and where surgery is the right answer, the right surgery is the one that does only what is necessary, with maximum precision. We avoid operating where conservative management works and we plan surgery where it is genuinely warranted.
Aligned with AAGL, ESGE & RCOG guidance
A structured 45–60 minute consultation. We listen to the full history, review prior records, examine where appropriate, and discuss the next step in plain language. You leave with a written plan and a clear understanding of timing, costs, and options.
If you are weighing a major treatment decision — surgery, IVF, hysterectomy — a structured second-opinion consultation is one of the most valuable things you can do. Bring prior reports. We will give you our honest reading without pressure to switch your primary care.
In short
Laparoscopy is keyhole surgery for gynaecological conditions — endometriosis, fibroids, ovarian cysts, adhesions and hysterectomy where it is genuinely indicated. At Balaji Horizon in Ahmedabad it is performed by Dr. Priyadatt Patel, MS, who holds the Diploma in Gynaecological Endoscopy from the Kiel School of Gynaecological Endoscopy (Germany) and the Part 1 Diploma in Operative Endoscopy, ESGE-CICE (France). Surgery is recommended only when it changes the outcome; conservative options are discussed first.
Laparoscopy — also called minimal-access surgery or keyhole surgery — is performed through three or four small incisions (5–10 mm) using a high-definition camera and specialised long instruments. The abdomen is gently distended with carbon dioxide to create a working space. The surgeon operates while viewing a magnified, high-resolution image on dedicated monitors.
Compared with traditional open surgery, laparoscopy offers materially better outcomes: less blood loss, less pain, faster recovery, fewer adhesions, smaller scars, and shorter hospital stay. For gynaecologic procedures specifically, modern evidence (Cochrane reviews, ESGE, AAGL) supports laparoscopy as the preferred approach for almost all benign indications — including endometriosis, fibroids, ovarian masses, ectopic pregnancy, hysterectomy, and tubal procedures.
But laparoscopy is not a “trick” or a marketing label. The quality of outcome depends on surgeon training, anatomical respect, energy-source technique, and proper patient selection. A laparoscopic approach performed poorly is worse than an open surgery performed well.
The clinical and outcome differences between laparoscopic and open gynaecologic surgery are well-documented across decades of studies. For women in reproductive age with benign disease, laparoscopy is the standard of care wherever feasible.
Magnified visualisation enables precise haemostasis. Blood loss in laparoscopic procedures is typically a fraction of open equivalents.
Hospital stay typically 24–48 hours vs 5–7 days for open. Return to normal activity within 7–14 days for most procedures.
Reduced tissue trauma, less peritoneal exposure, and gentle instrumentation lead to substantially fewer post-operative adhesions — critical for future fertility.
Smaller incisions, less tissue exposure, and shorter hospitalisation reduce surgical-site infection rates.
10× magnified high-definition view allows identification of subtle pathology (small endometriotic implants, fine adhesions) often missed at open surgery.
Small port-site scars (5–10 mm) replace large abdominal scars — important for younger patients and for psychological recovery.
Fibroids are among the most common conditions we treat this way — see our dedicated approach to uterus-sparing fibroid surgery (myomectomy) in Ahmedabad.
The range of gynaecologic conditions amenable to laparoscopic management has expanded substantially over the last two decades. At Balaji Horizon, we offer laparoscopic management for the full spectrum of benign gynaecologic conditions.
Excisional surgery for peritoneal, ovarian, and deep infiltrating endometriosis. Fertility-sparing technique with ovarian reserve protection. Endometriosis programme →
Laparoscopic myomectomy for symptomatic fibroids in women wishing to preserve fertility. Suitable for most intramural and subserosal fibroids. Hysteroscopic approach for submucous fibroids. Fibroids guide →
Benign cysts (dermoid, endometrioma, simple cysts) managed with laparoscopic cystectomy — preserving healthy ovarian tissue and protecting reserve.
Salpingectomy or salpingostomy for tubal ectopic pregnancy. Faster recovery and lower morbidity vs open. Tube preservation in selected cases.
Total laparoscopic hysterectomy (TLH) for indicated benign conditions — adenomyosis, large fibroids, persistent abnormal bleeding when conservative options have failed. Always a considered decision, never first-line.
Salpingostomy, salpingectomy, tubal reanastomosis (reversal of sterilisation in selected cases). Hydrosalpinx management before IVF.
Adhesiolysis for dense pelvic adhesions causing chronic pain or infertility — particularly post-surgical or post-infection adhesions.
Most laparoscopy worldwide is still 2D — flat, depth-perception-deprived imaging that forces surgeons to estimate spatial relationships. The Karl Storz 3D laparoscopy system from Germany delivers genuine stereoscopic 3D visualisation, restoring the surgeon’s natural depth perception. This is not a software trick or “3D-like” enhancement — it is dual-channel optics with polarised displays, the same principle as the human eye.
Native stereoscopic vision restores natural spatial judgement — critical for tissue plane identification in endometriosis and deep pelvic disease.
Intra-corporeal suturing — myomectomy closure, uterosacral reattachment, tubal repair — is materially more accurate with true 3D.
Published studies (J Minim Invasive Gynecol, Surg Endosc) show shorter operative time and fewer instrument-tissue collisions with 3D vs 2D systems.
Karl Storz is the global gold-standard manufacturer of endoscopic equipment — the same systems used in leading academic centres across Europe and the US.
Investment in 3D is not about marketing — it is about the surgical decisions it enables. For excisional endometriosis surgery, deep infiltrating disease, and any procedure requiring fine suturing, true 3D visualisation translates to measurable outcome differences.
General anaesthesia administered via dedicated anaesthesia workstation with ventilator. Pre-operative anti-emetic and analgesic protocols.
Three or four small incisions (5–10 mm) — usually one at umbilicus and two/three in the lower abdomen. Sites chosen for procedure-specific access.
Carbon dioxide gas at low pressure (10–12 mmHg) gently distends the abdomen creating working space.
Karl Storz 3D camera + specialised long instruments. Energy sources (bipolar, ultrasonic) used selectively for haemostasis and dissection.
Excised tissue retrieved via endobag through the umbilical port. Larger specimens (fibroids, hysterectomy) morcellated under contained conditions.
Port sites closed in layers with fine absorbable sutures. Recovery in PACU then ward. Most patients discharged within 24–48 hours.
Senior gynaecologist and advanced laparoscopic surgeon focused on minimal-access surgery for fibroids, ovarian cysts, endometriosis, adhesions and hysterectomy — with meticulous, fertility-sparing technique aligned to ESGE and AAGL standards.
For women of reproductive age, every laparoscopic decision is filtered through one question: will this preserve future fertility? Surgeons trained in fertility-sparing technique build that consideration into every gesture — instrument selection, energy use, suturing approach, and timing of intervention.
Endometrioma cystectomy by stripping technique with minimal cautery near the ovarian hilum. Bipolar energy used sparingly; haemostasis preferentially achieved by gentle pressure or fine suturing. AMH documented pre-op and at 3 months post-op.
Atraumatic tissue handling, copious irrigation, meticulous haemostasis, and selective use of adhesion barriers. Smaller raw surfaces, less peritoneal damage — measurably fewer postoperative adhesions.
Layered closure of the uterine defect with fine sutures. Karl Storz 3D depth perception meaningfully improves intra-corporeal suturing precision — important for future pregnancy and reduced risk of uterine rupture.
First surgery is the best surgery. Repeated operations on the same ovary cause cumulative reserve loss. Patient selection, complete excision when indicated, and post-surgical hormonal suppression where appropriate — to reduce recurrence and re-operation need.
Ambulation within 4–6 hours. Oral fluids on the same day for most procedures. Pain managed with multi-modal analgesia.
Discharge for most laparoscopic procedures. Diet advanced to regular. Driving and light activity from day 3–5 in most cases.
Return to work for desk-based roles. Heavy lifting and strenuous exercise restricted for 4–6 weeks.
First post-op review. Histology report discussed. Long-term plan reviewed — including conception timing, medical management, and follow-up cadence.
Minimal-access, organ-sparing surgery with a clear, honest plan built around your priorities — alongside the WhatsApp and phone options above.
Book a consultation| Laparoscopic (key-hole) | Open surgery | |
|---|---|---|
| Incisions | A few 5–10 mm ports | A single large incision |
| Blood loss | Usually less | Typically more |
| Hospital stay | Often 1–2 days | Generally longer |
| Recovery | Days to a couple of weeks | Several weeks |
| Magnified view | Yes — 3D, high-definition | Direct vision only |
| Best suited to | Most benign gynae & endometriosis surgery | Selected complex or malignant cases |
Laparoscopy is not automatically superior for every case — the right approach depends on the condition, anatomy and goals.
Laparoscopy has an excellent safety profile in trained hands. Complications are uncommon and typically less severe than open surgery. The procedure requires general anaesthesia by a qualified anaesthetist, and is performed in a fully equipped operation theatre with Class 100 air standards.
Standard 2D laparoscopy loses depth perception — surgeons compensate by inference. True 3D (such as Karl Storz 3D) restores stereoscopic vision, improving spatial accuracy especially for excisional endometriosis surgery, intra-corporeal suturing, and deep pelvic dissection. Published studies show shorter operative times and fewer instrument-tissue collisions.
Scars are small (5–10 mm), placed at the umbilicus and lower abdomen. Over 6–12 months they typically fade to fine lines and are far less visible than an open surgery scar.
Most laparoscopic procedures: 24–48 hours. Complex DIE or extensive myomectomy: 48–72 hours. Day-care procedures (diagnostic laparoscopy, simple cystectomy) may be same-day discharge.
Depends on procedure. After endometriosis excision or salpingostomy — typically 4–8 weeks. After myomectomy — usually 3–6 months for the uterus to heal. Individual timing depends on procedure complexity and intra-operative findings.
All surgery carries risk. Laparoscopy-specific risks include: trocar injury (rare), gas embolism (very rare), conversion to open surgery (1–3% depending on procedure), and complications related to anaesthesia. Specific procedures carry specific risks (e.g., ureteric injury in DIE surgery). These are discussed transparently at consultation.
For most benign gynaecologic indications, outcome data does not show robotic surgery to be superior to advanced laparoscopy in experienced hands. Robotic systems offer some ergonomic and 3D advantages. Karl Storz 3D laparoscopy delivers similar visualisation benefits at a fraction of the cost.
If ovaries are preserved (the default for premenopausal women) hormonal function continues normally. Only if both ovaries are removed (oophorectomy) does menopause begin — and that decision is made carefully based on age, indications, and risk-benefit.
Yes — fibroids up to 10–12 cm in selected positions can be removed laparoscopically by an experienced surgeon. Very large, very numerous, or deep intramural fibroids may require open myomectomy. Decision depends on size, number, location, and surgeon’s experience.
All prior ultrasound/MRI reports and image files, any previous operation notes, medication list, AMH report if recent, and a clear understanding of your fertility plans and priorities.
ADVANCED LAPAROSCOPIES
Programme lead caseload
HD LAPAROSCOPY ENABLED
+ AAGL ALIGNED PROTOCOLS
BV + UKAS CERTIFIED
PRINCIPLED MEDICINE · NOT PROMOTION
PATIENT PATHWAY
Surgery is offered only when conservative options have been weighed and clinical indication is clear. Symptom severity, imaging findings, fertility goals, and prior treatment response all enter the decision.
Advanced ultrasound (per ISUOG IDEA for endometriosis), MRI when indicated, baseline AMH and AFC for ovarian reserve, full bloods, and cardiopulmonary workup tailored to age and history.
Complex cases involving bowel, bladder, ureter, or nerve planes are planned with colorectal, urology, and pelvic-pain anaesthesia colleagues from the outset, not mid-procedure.
Procedure performed with precise instruments, 3D HD vision where applicable, complete excision over ablation, fertility-preserving technique. Same-day to short-stay recovery for most cases.
Per ESHRE: endometriosis surgery is one part of long-term, individualised management – not an endpoint. Hormonal therapy, fertility planning, and structured follow-up continue post-operatively.
When performing surgery for ovarian endometrioma, specific caution should be used to minimize ovarian damage.
What this means for you: an endometrioma (‘chocolate cyst’) does not always need an operation. The decision depends on your pain, your age, your egg reserve (ovarian reserve), any previous surgery and your plans for pregnancy. Before IVF, removing an endometrioma is not routinely advised just to improve the chance of a baby. It may still be considered for pain, or if the cyst would make egg collection difficult. If surgery is chosen, it is planned to protect the healthy ovary.
Updated 12 October 2026: we removed a quotation attributed to an “ESGE Guideline on Endometriosis Surgery, 2023”, which we could not trace to any published guideline, and replaced it with a recommendation from the ESHRE guideline on endometriosis (2022), with a link to its source and a plain-English explanation.
Tell us the main issue to see how we generally approach it. Educational only — not a diagnosis.
This interactive guide is educational and does not replace a clinical assessment or imaging review. It cannot diagnose your condition. Please discuss your situation with Dr. Priyadatt Patel at Balaji Horizon Women’s Hospital.
Surgery is not always the answer. We operate only when there is a clear indication, after evaluating whether medical management or watchful monitoring is the safer first step — and we plan every procedure around your fertility goals and ovarian reserve. The aim is the least intervention that achieves a durable result, not the largest one.
Mild pain, shoulder-tip ache and tiredness are expected for a few days. Contact us or attend emergency if you develop:
Call +91 97234 31544; for breathlessness or chest pain, go to the nearest emergency department immediately.
Standard post-operative warning signs (wound infection, ileus, VTE) per RCOG/AAGL day-surgery safety guidance.
Surgery is the right tool for some situations and the wrong one for others. Select what applies — we'll show how the decision is usually approached. Education only, not a diagnosis.
Tap what applies above.
Aligned with ESGE/AAGL and NICE principles — surgery only with a clear indication; for endometriosis/cysts, ovarian reserve is protected at every step.
Symptoms, previous treatment and your priorities, including fertility, discussed with Dr. Patel.
Detailed ultrasound, and MRI when needed, to map the problem before any decision.
Surgery only where it adds value, with non-surgical options and risks explained.
Precise laparoscopic or hysteroscopic surgery, protecting fertility wherever possible.
Post-operative review, results explained, and a long-term plan to reduce the need for repeat surgery.
Questions about your situation?
Our team will call you back during clinic hours (Mon–Sat). No obligation.

ISO 9001:2015 Certified · State Registered
ISO 9001:2015 Quality Management System — UKAS Accredited Certification by Bureau Veritas
Certificate IND.25.899/QM/U · Valid until 02 September 2028 · Independently verify at certcheck.ukas.com
Permanently registered under Gujarat Clinical Establishments Act, 2021 · Reg. No. CEA/AHD/262/2025 · Single Speciality Hospital · 15 Beds
Operated by Balaji Women’s Clinic · Trading as Balaji Horizon Women’s Hospital
Reviewed by Dr. Priyadatt Patel. New patient guides, clinical FAQ updates and quiet clinical notes. No promotional spam.